

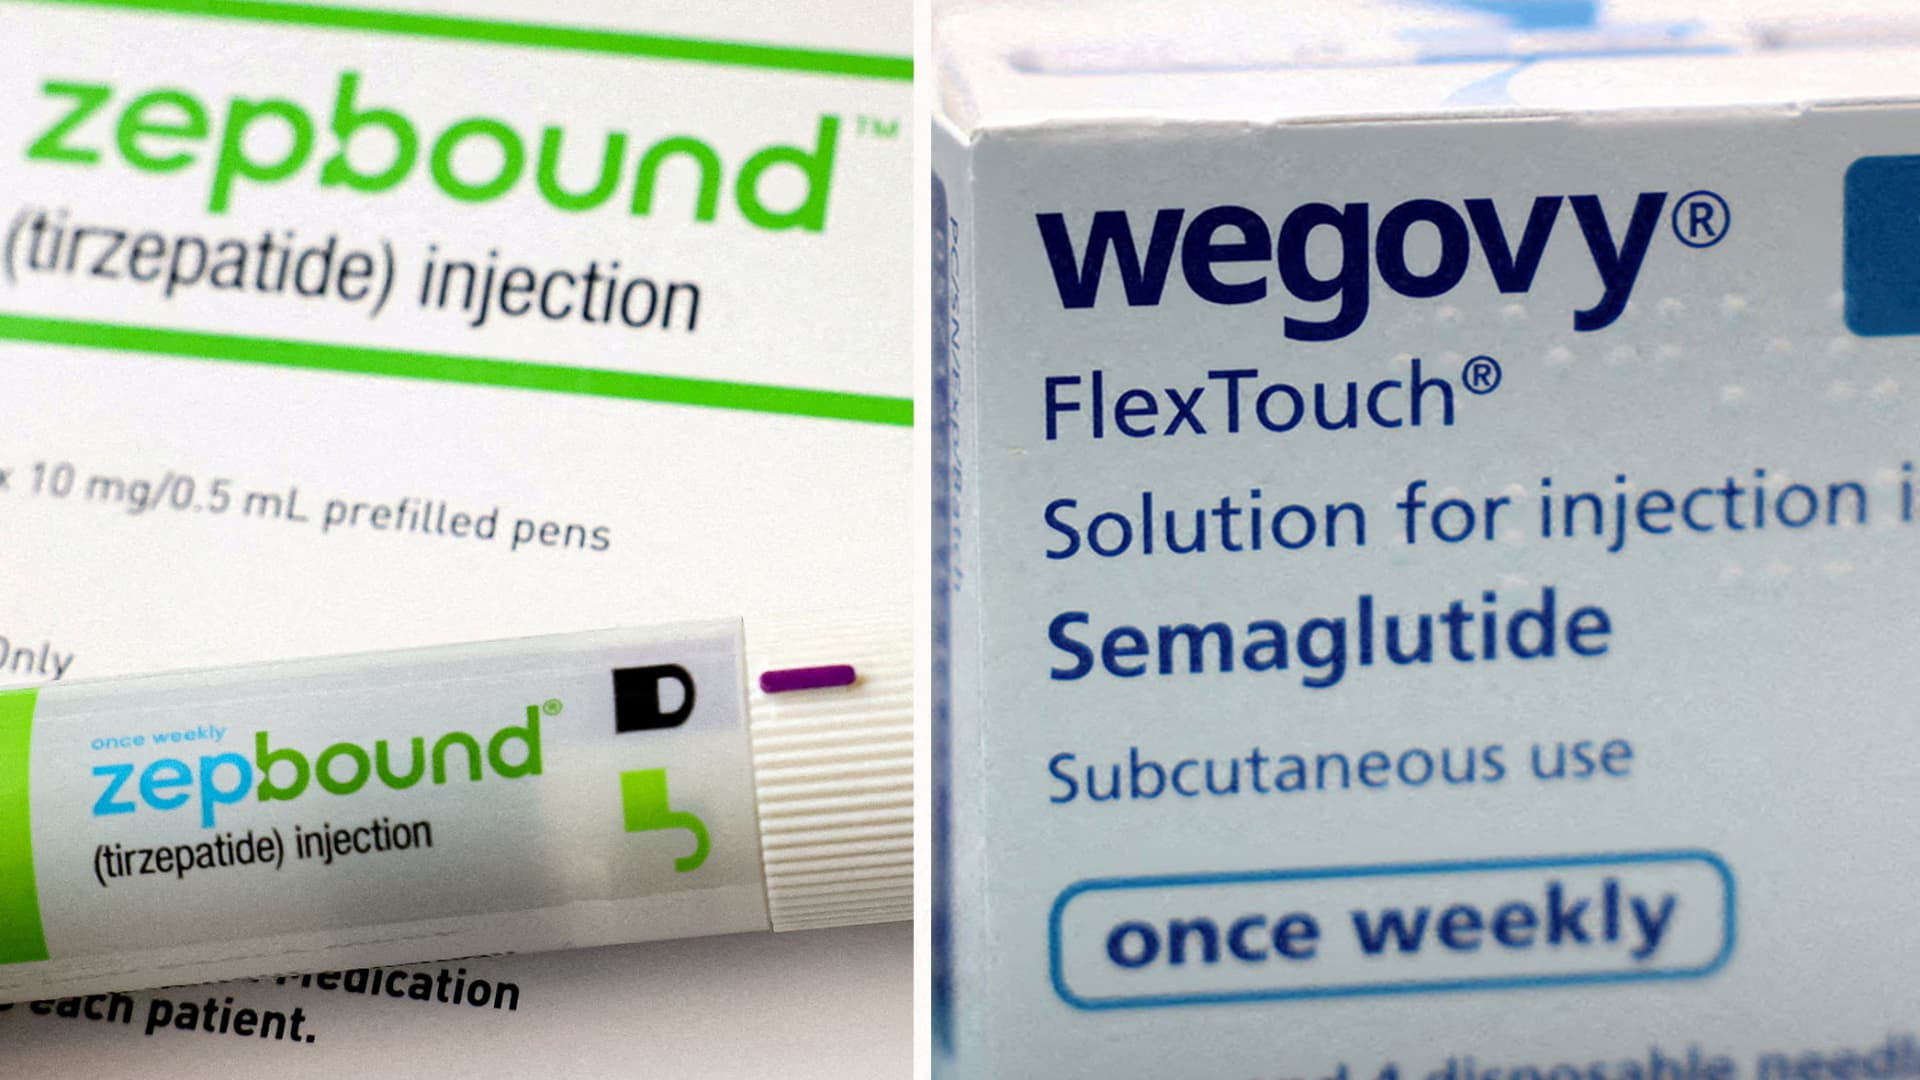

With open enrollment season in full swing, many employees may have noticed something noticeably missing from their benefits menu: coverage for GLP-1 drugs for weight loss.
More companies are eliminating coverage entirely or paying employees less. In some cases, they are moving to a completely different model, offering employees a type of consolation prize and giving them access to weight management programs through third parties.
Coverage for these drugs for weight loss is expensive for employers, typically costing between mid-$500 and mid-$600 per user per month. Some companies say it’s worth covering medicines at any cost for the health of their employees. “We’re spending about $250 million or more on GLP, and that’s up from zero,” Bank of America CEO Brian Moynihan told CNBC’s Andrew Ross Sorkin in August. “We can see that it’s having a huge impact on our employees. … Believe me, we’re trying to burden everyone with the price and make it as cheap as possible (as much as possible). But in our view, in addition to the long-term health benefits, there may be even more short-term health benefits … It’s a good investment.”
Nevertheless, as health care costs continue to rise, more employers are seeking exits from GLP-1 coverage for weight loss, including large corporations. According to WTW’s Annual Health Benefits Survey, conducted over the summer and published in full on Wednesday, 53% of employers with 100 or more employees have GLP-1 coverage for weight loss, down from 57% in 2025. This is the first decrease in three years. Additionally, 16% of employers say they currently have drug coverage but are considering lifting it, up from 9% last year.
A recent Marsh survey of more than 1,800 U.S. employers found that health insurance costs per employee are expected to rise by an average of 8.2% in 2027, the largest increase since 2003, with GLP-1 use accounting for a full percentage point of overall cost growth. The company’s experts cite rising costs as one reason employers are considering discontinuing coverage in 2027.
“Employers are very concerned about the balance between empathy and economics,” said Caroline Susie, director of integrated health management at Marsh.
Some workers with employer-provided health insurance have options in case GLP-1 coverage is discontinued, but there may not be anything comparable to full health insurance coverage. Here are some promising alternatives:
Direct-to-consumer program
Some employers are directing workers to purchase GLP-1 through direct-to-consumer options such as Novo Nordisk’s NovoCare and Eli Lilly’s LillyDirect. According to WTW research, 8% of employers have adopted this approach, and 28% are planning or considering it.
Seth Friedman, Gallagher’s pharmacy and health plans practice leader, estimates that 20% to 30% of his company’s customers will discontinue coverage in 2027, sending employees into the direct route. For employers, this move means significant savings. According to Gallup, the percentage of U.S. adults taking GLP-1 drugs for weight loss will rise to 11% in 2026, up from 3% in 2024. Additionally, 15% reported having used the drug for weight loss, an increase of 9 percentage points.
“Many people will choose to pay for it themselves, even if it’s not covered by their plan,” said Jeff Levin Schertz, population health leader at WTW.
The starting price for the lowest dose of Novo’s WeGoBe for self-pay individuals is currently $149 per month for tablets and $199 per month for injectables. These prices are subject to change in 2027. Novo Nordisk states that current promotional prices are subject to change or discontinuation. Lilly’s Zepbound starts at $299 per month for single-dose vials or multi-dose KwikPens.
Direct to Employer Program
Some companies are moving away from traditional pharmacy program coverage and toward an employer-direct model that reimburses a portion of employees’ out-of-pocket costs.
“These ‘alternative coverage’ models allow employers to access more favorable pricing and greater control over contributions without having to cover drugs on the PBM formula,” said a spokesperson for Vida Health, one of several vendors working with employers in this area. Others include Noom and GoodRx.
Employers can often design programs tailored to their employees’ needs at significant savings over paying for GLP-1 drugs through a pharmacy benefits manager, said Alisha Furno, Marsh’s national pharmacy practice leader. A PBM is a third-party administrator that manages prescription drug benefits for health insurance companies and employers.
Based on direct-to-consumer prices, employers can fully subsidize and pay vendor fees for far less than, say, purchasing Wegovy through a PBM, according to WTW’s Levin Schertz.

weight management program
Some employers are eliminating coverage and contracting with third parties, such as CVS Weight Management, Noom, Omada Health, UnitedHealthcare, Vida, and Virta, to provide weight management programs to their employees. Some employers previously offered this type of program, while others made the program available only after eliminating GLP-1 coverage for weight loss.
According to Marsh’s 2025 data, 25% of employers with 500 or more employees hired vendor partners for lifestyle modification and nutritional support. The cost of these programs is typically borne by the employer, not the employee, and provides significant savings compared to GLP-1 coverage. Services vary by member, but typically include live or online coaching on behavior change, diet, exercise, nutrition, and other health topics. Marsh’s Susie said these programs can cost about $65 to $100 per employee per month, depending on what is offered. Employers who choose a vendor that also provides prescription services may pay upwards of $150 per month per participating employee.
Service providers have cited positive results from their programs in recent years. Omada Health data shows that 63% of members evaluated 12 months after discontinuing GLP-1 maintained or continued to lose weight. Data from United Healthcare’s Real Appeal program shows that 88% of at-risk participants lost weight during a 52-week program aimed at promoting healthy eating, physical activity, increased feelings of well-being, and improved health outcomes. Additionally, 37% of participants lost more than 5% of their body weight. Meanwhile, initial program results reported by CVS Weight Management showed that members maintained 90% of their weight loss 10 to 12 months after completing drug therapy.
The services offered by providers vary somewhat, but often feature professional support. “We want to make sure that if we take GLP-1 off for any reason, the behavioral changes are maintained,” said Cody Fair, Noom’s chief commercial officer. “We were able to lose weight because they retrained their brains and changed their habits,” he says.
But employee utilization can be a challenge, Gallagher’s Friedman said. “It’s totally a commitment, and that’s probably why not many people do it, especially when you know you can have a doctor write a script and go straight to Novo or Lilly.”
FSA, HSA funds for medically necessary GLP-1
Although these tax-advantaged accounts are not the only substitutes for comprehensive health insurance, GLP-1 drugs are eligible for Flexible Spending Account (FSA) and Health Savings Account (HSA) reimbursement when prescribed by a licensed health care provider to treat a diagnosed medical condition, such as obesity. The downside to using an HSA to pay for your GLP-1 is that the dollars you invest don’t have the opportunity to grow so they can be used tax-free in retirement.
The annual employee contribution limit to an FSA is $3,400 in 2026. The annual HSA contribution limits set by the IRS in 2026 are $4,400 for individuals with self-only coverage and $8,750 for individuals with family coverage. In 2027, the price will rise to $4,500 for individuals and $9,000 for families. The 2027 IRS contribution limits for FSAs have not yet been officially announced.
“Benefits are there to cover these out-of-pocket costs,” said Andrew Stocker, president of employee benefits at Boya Financial. “Employers need to educate their employees about the benefits that actually exist.”

